
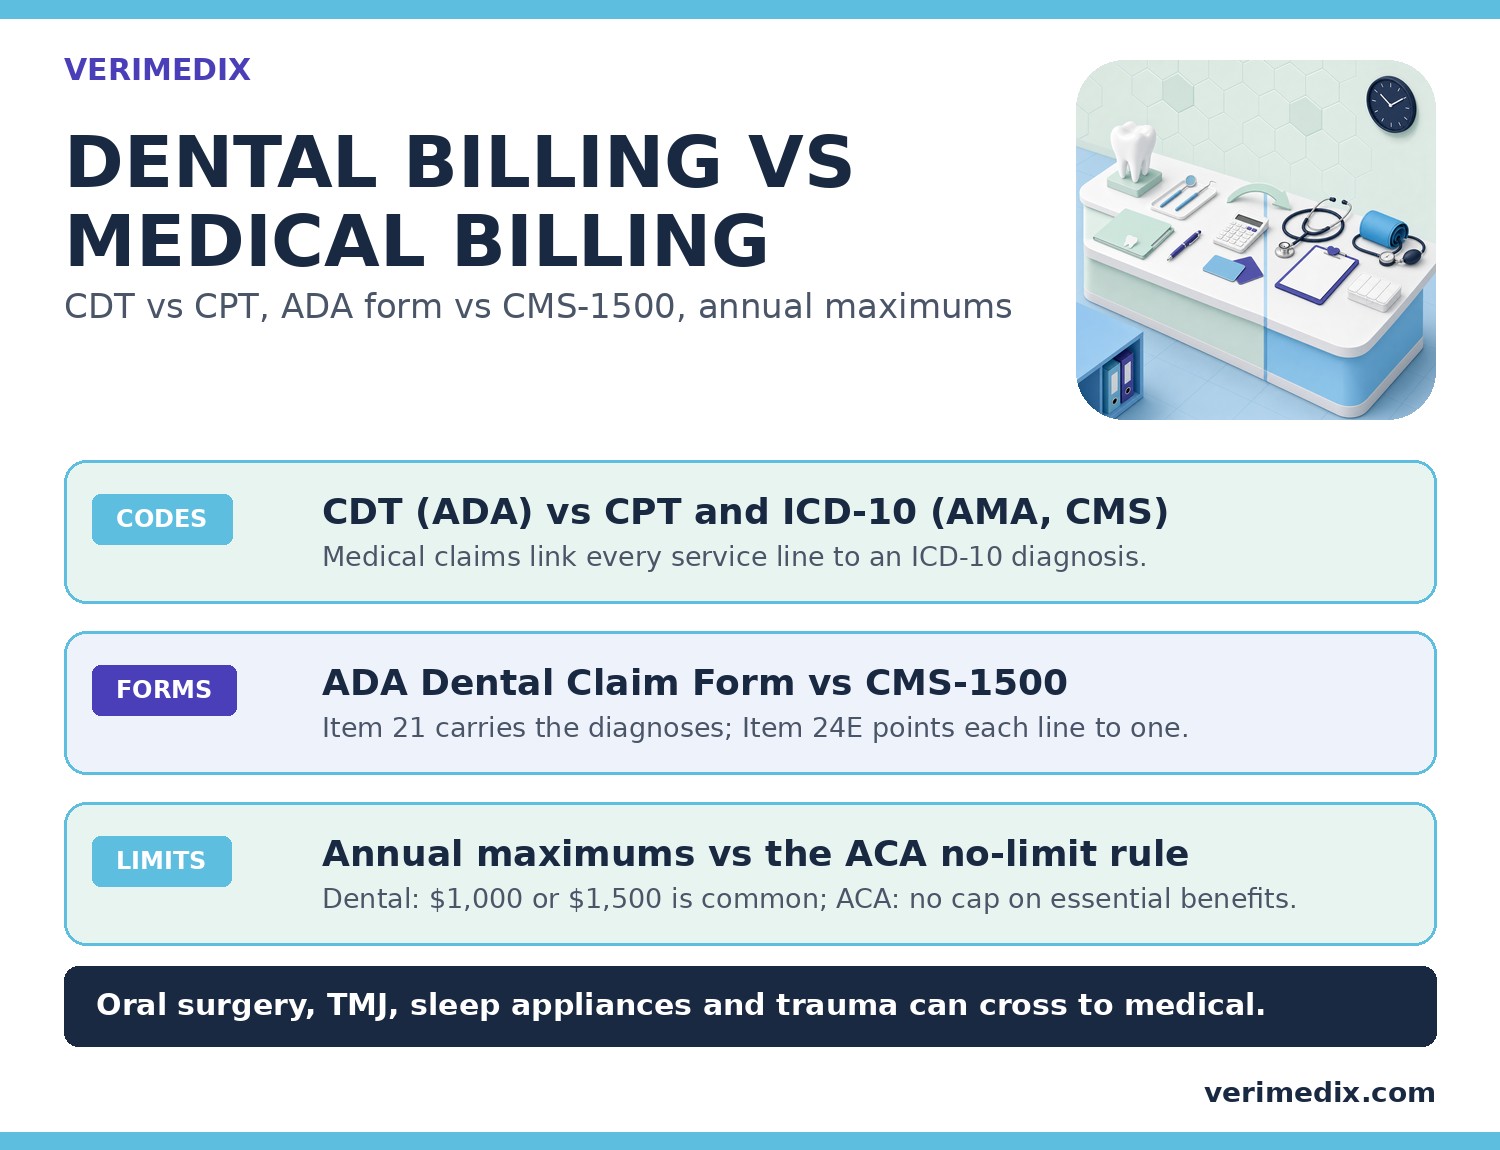
- Dental billing uses CDT codes (ADA) and the ADA J430D claim form; medical billing uses CPT codes (AMA), ICD-10 diagnoses, and the CMS-1500 form.
- Most dental PPO and indemnity plans cap what they pay each year (NADP notes that DHMOs rarely carry an annual maximum): the ADA calls a $1,000 or $1,500 annual maximum common and $2,000–$3,000 plans not uncommon, and NADP reports about 65% of dental PPOs at $1,500 or more; many plans follow a 100/80/50 coverage structure.
- ACA-regulated medical plans may not put an annual dollar limit on essential health benefits (45 CFR 147.126).
- Some dental procedures — oral surgery, TMJ, sleep apnea appliances, biopsies, trauma — qualify for medical reimbursement.
- Cross-coding to both dental and medical insurance can significantly increase revenue per procedure.
- Medical billing adds compliance layers: required ICD-10 codes, stricter medical-necessity documentation, and Medicare NCDs/LCDs or the payer’s own medical policy.
The Core Difference: Code Systems
The most fundamental difference between dental and medical billing is the procedure code set used:
- Dental billing uses CDT codes (Current Dental Terminology) — "D" codes developed and maintained by the American Dental Association
- Medical billing uses CPT codes (Current Procedural Terminology) — 5-digit numeric codes maintained by the American Medical Association
These code systems reflect the different clinical environments and payer expectations of each discipline. Dental codes describe dental procedures in ADA-standard terminology; medical codes describe a broader universe of medical, surgical, and diagnostic services.
| Feature | Dental Billing | Medical Billing |
|---|---|---|
| Code system | CDT codes (ADA) | CPT codes (AMA) |
| Diagnosis codes | Not always required | ICD-10 codes required |
| Claim form | ADA J430D | CMS-1500 |
| Primary insurer | Dental insurance plan | Medical insurance plan |
| Coverage scope | Dental procedures | Broad healthcare services |
| Annual maximums | Common ($1,000–$1,500 typical; $2,000–$3,000 not uncommon) | Not permitted on essential health benefits in ACA-regulated plans |
| Coverage complexity | Simpler benefit structures | Complex, highly variable |
How Dental Insurance Works Differently from Medical Insurance
Dental insurance typically covers a defined set of preventive, basic, and major services up to an annual maximum benefit. The ADA’s Dental Benefits: An Introduction calls $1,000 or $1,500 a common annual maximum and says plans at $2,000 or $3,000 are not uncommon; the National Association of Dental Plans reports that about 65% of dental PPOs now carry a maximum of $1,500 or more, and that fewer than 5% of enrollees reach it in a year. Many PPO and indemnity designs follow a 100/80/50 structure:
- 100% coverage for preventive services (cleanings, X-rays, exams)
- 80% coverage for basic restorative (fillings, extractions)
- 50% coverage for major restorative (crowns, bridges, dentures)
Medical insurance covers a much broader range of services with different cost-sharing structures (deductibles, co-pays, co-insurance) and typically does not have annual maximums. For plans regulated by the Affordable Care Act that is a rule, not a habit: a group or individual medical plan may not set an annual dollar limit on essential health benefits (45 CFR 147.126). Stand-alone dental coverage is a “limited scope” excepted benefit (45 CFR 146.145 for group plans), which is why the annual maximum survives on the dental side.
When Dental Practices Should Use Medical Billing
Some dental procedures qualify for reimbursement under a patient's medical insurance — either because they're medically necessary or because they relate to a systemic health condition. These include:
- Oral surgery (tooth extractions, bone grafts, implant placement) when medically indicated — our oral surgery cross-coding guide walks the medical-versus-dental decision procedure by procedure
- TMJ treatment — billed to medical under musculoskeletal diagnosis codes. A night guard for grinding is a different appliance from a TMD splint, and our night guard dental code guide separates D9944–D9946 from the D7880 occlusal orthotic.
- Sleep apnea oral appliances — billed to medical under sleep-disorder diagnosis codes (for example ICD-10-CM G47.33, obstructive sleep apnea). For Medicare, the DME MAC LCD L33611 covers the custom appliance (HCPCS E0486) only when the treating practitioner — an MD, DO, nurse practitioner, physician assistant or clinical nurse specialist, never the dentist — orders it after reviewing the sleep test report, and a licensed dentist provides and bills it; the diagnostic side of that pathway is what our sleep medicine billing services cover.
- Periodontal treatment in diabetic or cardiovascular patients — often billable to medical
- Biopsies and lesion removals — typically billable to medical
- Trauma-related dental procedures — often medical-billable depending on cause
Cross-coding — billing to both dental and medical insurance where appropriate — can significantly increase revenue per procedure for practices in oral surgery, periodontics, and sleep dentistry.
Either way, getting paid in network starts with being credentialed with each payer. See our guide to dental credentialing and payer enrollment.
Regulatory Differences: HIPAA and Compliance
Both dental and medical billing are subject to HIPAA regulations covering patient data privacy and security. However, medical billing involves more complex compliance layers:
- Medical billing requires ICD-10 diagnosis codes on every claim, linking the procedure to a medically documented condition
- Precertification and medical necessity documentation are more rigorously required in medical billing
- Coverage rules come from different places. For Medicare, National Coverage Determinations (CMS) and Local Coverage Determinations — a Medicare Administrative Contractor’s decision on whether a service is reasonable and necessary in its jurisdiction (42 CFR 400.202) — decide coverage, and most dental services are excluded by statute (Social Security Act §1862(a)(12)), with exceptions CMS lists for dental work inextricably linked to a covered medical service such as an organ transplant, cardiac valve replacement or head and neck cancer treatment (CMS, Medicare Dental Coverage). Medicaid dental coverage is set state by state: children’s dental benefits are required under EPSDT, while each state chooses whether to cover adult dental care (Medicaid.gov). Commercial medical plans publish their own medical policies.
Dental practices venturing into medical billing must invest in proper coding training, documentation protocols, and compliance processes to avoid claim denials and audit risk.
What a Medical Claim from a Dental Office Needs
Cross-coding fails at the front desk more often than at the coder’s desk. Before the appointment, run insurance eligibility verification on the patient’s medical plan, not just the dental plan: whether the procedure is a covered benefit, where the patient stands against the medical deductible, and whether the plan wants prior authorization. A dental plan’s verification tells you nothing about any of those.
On the claim itself, the CMS-1500 is built around a diagnosis-to-procedure link that the ADA Dental Claim Form asks for only in defined cases: its diagnosis Items 34 and 34a (up to four ICD-10-CM codes, pointed to from Item 29a) are required when the diagnosis may affect adjudication or a state program or payer contract demands them (ADA completion instructions, version 2024). Medicare’s instructions for the form (Medicare Claims Processing Manual, chapter 26) have the diagnosis codes entered to the highest level of specificity in Item 21 and make Item 24E — the pointer that ties each service line to one of those diagnoses — a required field. Commercial medical payers read the same pointer. A medical claim that carries a procedure with no supporting diagnosis, or a diagnosis the payer’s policy does not accept for that procedure, is denied before anyone reads the chart notes.
Three more things the medical claim needs that a dental claim does not: the procedure reported with the CPT or HCPCS code the medical plan recognizes rather than the CDT code; a medical-necessity narrative in the record that connects the diagnosis, the findings (sleep test report, imaging, trauma history) and the treatment; and the referring or ordering practitioner’s name and NPI where the payer’s policy calls for an order — the Medicare oral-appliance rule above is the clearest example. Practices that cross-code regularly either train a biller on both code sets or hand the medical side to medical coding services that already work in CPT and ICD-10 every day.
Why Dental Billing Expertise Matters
Despite the apparent simplicity of dental insurance compared to medical, dental billing has its own complexity — CDT code changes, payer-specific rules, CDT/CPT crossover for oral surgery, and coordination of benefits for dual-coverage patients.
The best dental billing outcome comes from specialists who understand both code systems, know which procedures warrant medical billing, and can navigate the documentation requirements for both payers simultaneously.
At Verimedix, our dental billing team handles both dental insurance billing and medical cross-billing for dental procedures — helping practices collect every dollar they're entitled to from all available insurance sources.
Quick Answers
What is the difference between dental billing and medical billing? Dental billing reports CDT procedure codes on the ADA Dental Claim Form to a dental plan that usually carries an annual maximum; medical billing reports CPT or HCPCS codes linked to ICD-10-CM diagnoses on the CMS-1500 to a medical plan that pays on medical necessity.
Can a dentist bill medical insurance? Yes, for procedures the medical plan treats as medically necessary — oral surgery, TMJ treatment, sleep apnea appliances, biopsies and trauma care are the usual cases — provided the claim carries a supporting diagnosis and the plan’s documentation or order requirements are met.
Do dental plans really stop paying at the annual maximum? Yes, for plans that carry one. Once the plan has paid its annual maximum — commonly $1,000 or $1,500, with $2,000–$3,000 plans not uncommon per the ADA — the patient owes the rest of the year’s charges, which is why treatment planning around the maximum is a dental-office skill with no medical equivalent.
Does Medicare cover dental work? Mostly no: Social Security Act §1862(a)(12) excludes most dental services from Medicare payment. The broadest exception CMS lists is dental work inextricably linked to a covered medical service, such as clearing infection before an organ transplant or cardiac valve replacement. The custom oral appliance for obstructive sleep apnea is a separate case: it is covered as durable medical equipment under the DME MAC LCD L33611, not as dental care.
Do LCDs apply to Medicaid? Not directly. Local Coverage Determinations are Medicare instruments issued by Medicare Administrative Contractors; Medicaid dental coverage is set by each state’s program, with children’s dental required under EPSDT and adult dental optional.
Frequently asked questions
The core difference is the code system: dental billing uses CDT codes (ADA) with the J430D claim form, while medical billing uses CPT codes (AMA), requires ICD-10 diagnosis codes, and uses the CMS-1500 form.
Some procedures qualify for medical reimbursement, including medically indicated oral surgery, TMJ treatment, sleep apnea oral appliances, periodontal treatment in diabetic or cardiovascular patients, biopsies, and trauma-related dental procedures.
Cross-coding is billing to both dental and medical insurance where appropriate. For practices in oral surgery, periodontics, and sleep dentistry, it can significantly increase revenue per procedure by capturing reimbursement from both payers.
Dental insurance typically follows a 100/80/50 coverage structure with an annual maximum — commonly $1,000 or $1,500, with $2,000–$3,000 plans not uncommon (ADA). Medical insurance covers a broader range of services with deductibles, co-pays, and co-insurance, and ACA-regulated plans may not place an annual dollar limit on essential health benefits.
Medical billing requires ICD-10 diagnosis codes on every claim, more rigorous precertification and medical-necessity documentation, and coverage rules that differ by payer: Medicare follows National and Local Coverage Determinations and excludes most dental care by statute, Medicaid dental coverage is set by each state, and commercial plans publish their own medical policies.